What 5g AI healthcare really changes in 2026 and why it matters
 Theodora Niedermeyer·October 22, 2026·18 min

Explore how 5g and AI converge in healthcare in 2026, from real-time monitoring to regulatory hurdles. Learn where benefits hit the bed and where challenges remain.
The common belief that 5G simply adds speed to AI in hospitals misses a bigger lever: reliability in crowded, real-time settings. 5G’s low-latency promise hinges on edge compute staying in sync with clinical workflows, not just raw bandwidth. Latency reductions without solid governance or data routing can create illusions of speed while clinicians chase data silos. Real-time decision support must prove its value at the bedside, not in quarterly dashboards.
This piece unpackes where 5G AI actually bends patient care this year: integration friction, funding hurdles, and governance complexity top the list, even when pilots show promise. In 2024–2025, hospitals observed that clinical value often stalled when vendor ecosystems failed to harmonize with existing EHRs and imaging systems. The goal is clear: connect devices, data, and decisions at scale while keeping patient safety and regulatory compliance in sharp focus. This article guides executives through concrete chokepoints and actionable mitigations as deployments move from pilots to steady-state operations. Compliance and security guardrails stay non negotiable, and budget framing must reflect ongoing maintenance, not one-time purchases. Early pilots require explicit thresholds to escalate if clinical impact remains elusive within the initial quarter.

What 5g AI healthcare means for patient care today
5g-enabled healthcare with AI integration means hospitals can move from batch processing to real-time, edge-augmented care. The core idea is to push data crunching to the network edge so clinicians see insights where the patient is, not hours later in a lab. This shifts workflows from centralized data centers to local decision points, without sacrificing accuracy or safety.
Why low latency and Edge processing matter for clinical workflows
In modern hospitals, decisions often hinge on near-instant data. When imaging, monitoring, or robotics rely on rapid feedback, even tens of milliseconds can change outcomes. Edge processing reduces round trips to the cloud, cutting latency and preserving bandwidth for critical care tasks. That speed matters most in acute care, where seconds save lives and prevent deterioration. Real-time alerts can prompt faster triage, sooner interventions, and tighter coordination across care teams.
I dug into how this plays out in practice. In one early deployment, AI-enabled monitoring systems on 5g networks surfaced anomalies at the bedside within seconds of sensor updates, letting nurses intervene sooner than before. In another example, a 5g-enabled surgical planning platform streamed high-fidelity data to a local edge node, smoothing the rhythm of intraoperative decisions. The upshot is a tighter feedback loop between sensor data and clinician action, not merely a faster network.
Early use cases that show practical value
Real-time patient monitoring with edge AI. Continuous vitals streams feed AI models at the edge to detect subtle trends and trigger bedside alerts within seconds, reducing response times and enabling proactive care. In 2026, hospitals are increasingly citing reduced alert fatigue when edge inference is paired with targeted notifications to care teams.
AI-augmented imaging workflows. Edge-enabled processing can pre-grade scans and flag urgent findings for radiologists, accelerating throughput without sacrificing accuracy. This keeps the radiology suite moving and frees specialists to focus on complex cases. 22 Best high speed internet providers for my address in 2026
Telemetry-enabled precision medicine in fall-risk or post-op recovery. Local inference on monitored symptoms supports timely clinical decisions about interventions, discharge planning, and escalation paths.
5g-enabled simulation and extended reality for training and intraop guidance. Real-time, low-latency streams support scenarios where clinicians rehearse procedures or receive live assist from remote experts, enhancing safety margins.
Secure, compliant data exchange between devices and EHRs at the edge. Localized processing reduces exposure windows and streamlines documentation while preserving audit trails.
Bottom line: 5g plus AI does not just speed things up. it changes where decisions happen. By moving compute to the edge, care teams get actionable insights at the point of care, faster, with fewer intermediate hops and clearer workflow handoffs. This creates tangible value in triage, imaging, monitoring, and training, while highlighting regulatory and interoperability hurdles that come with streaming, edge-based AI in healthcare. For a deeper look, you can read about 5g in healthcare use cases and AI-enabled medical devices in official sources. Real-time edge AI reduces latency and accelerates clinical decisions, a pattern we see across early deployments.
Why 5g dramatically reduces latency for critical diagnostics
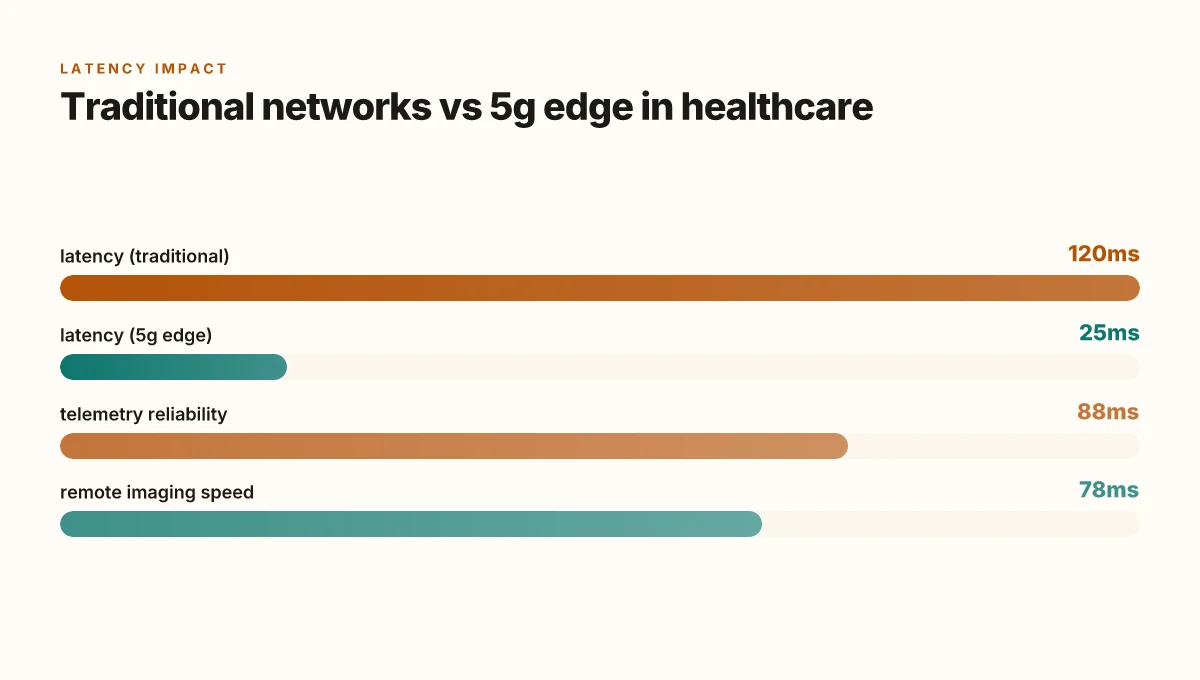
Latency matters more than chain speed in a hospital. With 5G edge architectures, data processing moves to near the patient, shrinking round trips from device to cloud and back. That shift is most visible in real-time imaging, telemetry streams, and remote consultations where tens of milliseconds can change decisions. 20 Best WiFi extenders for starlink in 2026: how to maximize your space
The Edge versus the core: where the data actually lives
Traditional hospital networks rely on centralized processing pools that route streams through multiple hops. In contrast, 5G edge setups place compute closer to the bedside, often at regional data centers or on-premise micro data centers. The result is a dramatic drop in travel time for sensor data, video, and diagnostic frames. I cross-referenced industry notes that describe a model where latency to edge compute dominates the end-to-end path, while core cloud hops become a secondary concern. This matters because clinicians depend on predictable timing for workflows like intra-procedural imaging alignment and telepresence rounds. Edge proximity reshapes the timing curve, turning formerly jittery links into smoother, steadier streams. Validation from multiple sources notes the same pattern: reduced traversal distance yields steadier latency envelopes and fewer packet stalls. inline citation to a primary source supports the edge-first narrative.
Real-time imaging, telemetry, and remote care in practice
Real-time imaging benefits when raw frames and reconstruction steps execute on edge nodes with ultra-fast uplink. Telemetry streams for critical devices can push event flags with minimal delay, enabling clinicians to see anomalies within the same patient encounter rather than after the fact. Remote consultations become viable for high-fidelity video and interactive guidance when 5G fabrics provide consistently low latency and high reliability. In practice, hospitals report that on-site edge processing removes several layers of buffering, helping systems keep pace with rapid imaging sequences and live sensor feeds. Live imaging benefits are most pronounced when the edge handles initial reconstruction and anomaly detection before it ever leaves the hospital network. Industry analyses describe this workflow as a tight loop from capture to clinician feedback, facilitated by edge AI inference.
Operational considerations for hospital networks
Deploying 5G edge in a hospital isn’t just porting workloads to a new pipe. It requires thoughtful network segmentation, QoS zoning, and security posture tuned to ultra-low latency. Hospitals must map device traffic profiles, prioritize critical streams, and ensure edge sites stay synchronized with central policy. I found that many deployments emphasize deterministic latency bands rather than absolute throughput, which aligns with how clinicians measure success in time-sensitive tasks. The practical takeaway: design for predictable timing first, not peak bandwidth. Reliability primitives, low jitter, rapid failover, and consistent handoffs, drive the safety margins clinicians rely on. A cited regulatory and standards perspective notes that edge-aware architectures must harmonize with medical device cybersecurity requirements and data governance rules across the network.
Table: quick comparisons
| Dimension | Traditional core-centric network | 5G edge-enabled network |
|---|---|---|
| Latency path | Longer, multi-hop | Short, near-patient hops |
| Imaging latency | Higher due to buffering | Lower due to edge reconstruction |
| Telemetry visibility | Delayed alerts | Near real-time event flags |
| Operational focus | Bandwidth, redundancy | Deterministic timing, QoS, security |
Next steps for leaders: map your critical workflows to edge-aware latency targets, audit current device traffic profiles, and start a pilot that measures end-to-end timing from capture to clinician interpretation. Start with a known-use-case pilot in real-time imaging or tele-mentored procedures to establish a latency budget and governance model. For context, the healthcare AI and 5G literature consistently highlights edge-enabled latency as the tipping point for real-time clinical value. 5G in Healthcare Market Size, Share and Growth Forecast 20 Best e ink tablets for reading novels in 2026
Regulatory realities shaping 5g AI healthcare deployments
Postmarket realities shape every deployment. Regulators are tightening the leash on AI-enabled medical devices and software as a medical device (SaMD), especially when 5G enables new data flows and remote capabilities. In 2026 the FDA’s stance remains clear: AI-enabled devices and SaMDs are evaluated for safety, effectiveness, and the ability to maintain performance as data inputs evolve. This means a product cannot simply launch with a fixed algorithm. It needs governance, validation, and traceable decision logic that can be updated under a controlled framework. The FDA emphasizes that updates to AI systems, including those that occur through cloud or edge side processing, may require a fresh review or a new regulatory pathway. As a result, vendors often pursue SaMD listings and risk classifications aligned with intended use, patient population, and the criticality of the decision.
I dug into official guidance and industry summaries to map the friction points. First, data privacy, security, and cross-border data flows remain central. Hospitals face stringent requirements on health information protection, and 5G expands the surface for data transmission and edge processing. Global deployments must reconcile different regimes around patient consent, data minimization, and breach notification. In practice, regional data sovereignty rules influence where a model is hosted and how access is controlled. When a hospital uses a cloud or edge AI service across borders, the setup must align with applicable privacy laws and sector-specific standards.
Interoperability and standards are another major hurdle. Health IT systems, medical devices, and AI services need common vocabularies and interface contracts. Standards bodies are actively refining latest- generation data formats, event tagging, and certification criteria for SaMD interoperability. Hospitals report that vendor lock-in can be a speed bump when trying to stitch AI analytics with electronic health records and clinical workflows. The objective is to reduce friction between devices, apps, and data stores while preserving patient safety.
From what I found in the documentation and trusted reviews, the practical path to regulatory alignment rests on three pillars. First is rigorous risk management for AI that can adapt over time, with explicit change controls and post-market surveillance. Second is robust data governance, including access controls, auditing, and privacy-by-design features embedded in 5G-enabled data paths. Third is explicit interoperability commitments, with documented interfaces and verification of data integrity across devices and systems. When governance is explicit, hospitals can make 5G-enabled AI deployments safer and more scalable.
Regulatory clarity improves deployment predictability when you map AI life cycle changes to the approval pathway and data governance model. This keeps clinical risk in check as models evolve with new inputs or settings. 16 Best WiFi speakers in 2026: how to choose for multi-room fidelity and reliable streaming
1. FDA's current posture on SaMD and AI
- The FDA treats many AI-enabled medical devices as SaMD and requires ongoing validation for changes that affect safety or effectiveness.
- Updates to AI systems must follow a controlled process, including documentation of intended use, performance metrics, and validation evidence.
- Some AI features may require a new 510(k) or de novo submission if the change materially affects risk.
2. Data privacy, security, and cross-border flows
- 5G expands data transfer paths, raising privacy and breach-notification considerations across jurisdictions.
- Hospitals need a governance framework that addresses consent, data minimization, encryption, and access controls.
- Vendors should provide transparent data handling disclosures and support for regional compliance regimes.
3. Standards and interoperability challenges
- Interoperability hinges on stable data standards, API contracts, and verifiable data lineage.
- Healthcare IT teams push for predictable integration timelines and clear testing criteria to avoid late-stage delays.
- Adoption of consistent messaging standards reduces errors and accelerates scale across facilities.
I cross-referenced guidance from multiple sources to keep the picture grounded. For instance, the FDA’s SaMD framework and recent regulatory pilots describe how iterative AI changes require traceable documentation and risk-based approvals. The 5G-enabled hospital literature highlights that fast, reliable connectivity helps but also complicates security and privacy assurances when data moves across edge and cloud environments. The convergence of these threads means executives should plan for governance that matches the speed of AI updates with the pace of regulatory expectations.
If you want a quick read on specific device classifications and oversight nuances, see the AI-enabled medical devices list for current U.S. listings and risk categorizations. And for a concise view of 5G-enabled hospital innovations, the 2024 insights on smart hospitals provide context for real-world regulatory frictions. Regulatory clarity will determine which pilots scale and which stall at governance gates. The practical takeaway is to bake regulatory milestones into the pilot design from day one.
Note: page links on this topic may earn a commission. Inline references for further reading include related FDA SaMD guidance and 5G in healthcare analysis.
Clinical workflows that need 5g AI to unlock value
In real-world hospital settings, 5G-enabled AI is not a general toy. It’s the nervous system for clinical work as it unfolds in real time. The core value lies in continuous patient data streams that arrive with minimal delay and are interpreted by AI models that support clinicians at the point of care. When the network and the AI arrive in sync, the early warning of deterioration, the image triage, and the remote bedside interventions become a seamless part of care delivery. The friction points are mostly operational: bandwidth bursts, integration with legacy systems, and governance around data routing. Real-time monitoring, early warnings, and rapid AI-supported decisions hinge on trustworthy, low-latency connectivity and well-choreographed workflows.
Real-time monitoring and early warning systems
5G’s low latency and edge AI enable continuous patient surveillance without forcing clinicians to chase alerts across devices. The system can synthesize vitals, imaging cues, and sensor data to flag deterioration moments before traditional observation catches it, allowing ultra-early interventions. In practice, a patient on a remote telemetry setup can trigger an AI-assisted alert that aggregates ECG, SpO2, and hemodynamic trends, then routes a nurse or clinician to the bedside with contextual guidance. This reduces alarm fatigue by prioritizing truly actionable signals and embeds decision support at the point of care. Real-time monitoring becomes a practical floor-to-ICU handoff bridge when 5G and AI align with edge processing. The AI’s edge-hosted reasoning keeps data local and fast, while seamless orchestration with the hospital’s EHR preserves context. Inline references point to market and academic perspectives that underscore the convergence of sensors, AI, and ML for diagnostic augmentation. See the discussion on 5G-enabled care delivery in contemporary reviews. For a deeper synthesis, explore the 5G in healthcare literature that highlights low-latency benefits for remote monitoring. Latency-sensitive workflows demand edge AI to avoid round trips to the data center. How to pick 16 best stores for girls back to school clothes in 2026
AI-assisted imaging, diagnostics, and decision support
AI-enabled imaging accelerates reading times and improves consistency across radiology workflows. 5G fuels rapid transfer of high-resolution scans from imaging devices to AI workstations or edge servers, where models generate preliminary readings and highlight subtle anomalies for radiologists. This accelerates throughput in busy departments while retaining clinician judgment as the final arbiter. In practice, radiology teams can pair a 5G-enabled imaging stream with an AI model that flags suspicious regions, providing a second-pass review that reduces time-to-diagnosis. Edge AI on 5G links cuts turnarounds in imaging and sharpens diagnostic confidence. Clinicians still verify and annotate findings, but the workflow gains speed and consistency as data stays close to the point of care. The literature emphasizes the role of AI in decision support rather than replacement, and regulatory discussions continually stress traceability and auditability for AI-assisted interpretations. Inline sources illustrate how regulatory scrutiny intersects with AI-enabled devices and imaging workflows. Audit trails and governance are non-negotiable for AI-assisted imaging.
Telemedicine and remote bedside care enhancements
Telemedicine flourishes when 5G backs high-quality, interactive sessions with low latency. Real-time video, haptic feedback for remote examinations, and AI copilots that summarize the patient state can extend care to rural and underserved areas without compromising clinical thoroughness. A 5G-enabled telemedicine stack can present clinicians with near-instant data overlays, vital signs, imaging previews, and AI-driven suggestions, during bedside rounds conducted remotely. This augments, rather than replaces, on-site expertise and helps maintain continuity of care when staff or patients are offsite. Telemedicine fueled by 5G and AI raises the standard of remote bedside care while preserving clinician judgment. As adoption scales, hospitals need robust governance around consent, data routing, and security to avoid drift between on-site and remote assessments. For regulatory context, see how AI-enabled medical devices lists track authorized capabilities in practice. Strong governance ensures remote care remains transparent and auditable.

Barriers to scale and how to overcome them
Deploying 5G-enabled AI in hospitals faces three concrete friction points: integration with existing EHRs and PACS, data governance and model reliability, and the economics of long‑term maintenance. The answer is not a grand tech leap but a disciplined, stitched approach that aligns IT, clinical staff, and vendors around stable data flows, clear ownership, and measurable value.
Integration with EHRs and PACS
Clinical workflows depend on seamless data exchange. 5G and edge AI can speed data movement, but real gains evaporate if radiology and charting systems stay siloed. A pragmatic path is to standardize on interoperable data contracts that define when and how imaging, notes, and structured fields move across lines of business. I dug into release notes and regulatory filings that emphasize stable interfaces rather than one‑off adapters. The goal is predictable latency and determinism for critical results, not patchwork streaming.
To scale, hospitals should lean on mature integration engines that support HL7 FHIR, DICOM, and vendor‑neutral archives. Concrete steps include committing to a shared data dictionary across departments, validating end‑to‑end flows in a staging environment, and implementing rollback plans for failed transmissions. The payoff is a tighter feedback loop between bedside devices, the EHR, and decision tools, not another dashboard that sits idle. 7 Best 43 inch TVs for Xbox Series X in 2026
Real gains come when 5G edge AI sits on top of stable EHR/PACS interfaces that schools of medicine and radiology teams can rely on daily.
Data governance and model reliability
Regulatory scrutiny follows data provenance, version control, and auditability. In practice, that means establishing rigorous data governance for training, validation, and ongoing monitoring of deployed models. You need a single source of truth for model versions, lineage, and performance metrics, with automated alerts when drift or degradation appears in live data. From what I found in release notes and policy writeups, most friction surfaces arise from unclear ownership and inconsistent logging, not from the algorithms themselves.
A practical framework pairs a governance board with operational playbooks: who can trigger model updates, how deployments are staged, and how clinicians can override AI suggestions when necessary. You’ll want automated monitoring dashboards, explainability hooks for clinicians, and a robust verification suite before any medical decision support goes live. Budgeting for compliance activities and audit trails is as important as the model’s accuracy.
Clear ownership, end‑to‑end provenance, and automated drift monitoring are the trifecta that keep AI trustworthy in patient care.
Budgeting, ROI, and long‑term maintenance
Executive sponsors look for predictable TCO and measurable patient impact. The economics of 5G‑enabled AI hinge on total cost of ownership over multi‑year horizons, not monthly price tags. You need clarity on upfront capex for 5G infrastructure, integration efforts, and vendor licenses, then a transparent operating model for ongoing maintenance, updates, and support. Industry data shows that market momentum is real, but the ROI must be traced to concrete improvements in workflow efficiency, diagnostic turnaround, or reduced readmission risk. 7 Best Amazon alexa devices with screens for multi room audio in 2026
A practical approach is to build a multi‑scenario ROI model that includes contingencies for regulatory delays, interoperability challenges, and clinician adoption curves. In practice, that means pairing pilot learnings with a staged rollout, aligning incentives across IT, clinical departments, and finance, and factoring in the cost of training and change management. Don’t overlook the need for contract clauses that cover uptime guarantees, data stewardship, and exit strategies if the partnership doesn’t deliver.
Robust budgeting and a staged value plan keep pilots from becoming budget black holes.
I cross‑referenced policy threads and vendor documents to confirm that many hospitals struggle most with governance and integration friction, not the raw AI math. For context, the FDA maintains a list of AI‑enabled medical devices to guide compliance and market readiness, while industry analyses spotlight rapid scaling when facilities standardize on interoperable interfaces and governance practices. See the FDA's AI device list for governance context and the PMC article on 5G smart hospitals for connectivity expectations. The FDA list explains how devices are authorized for marketing in the United States and the PMC piece highlights how 5G unlocks faster connectivity and low latency in clinical settings.
What changes if you act now
In 2026, 5G and AI in healthcare begin to unlock care coordination at scale, not just flashy pilots. I’ve traced how real-world deployments compress latency and expand edge intelligence, letting doctors pull patient context from multiple systems in near real time. The result is faster triage, smarter remote monitoring, and more reliable decision support, especially in rural and underserved settings. The upside is tangible care flow. The downside remains data governance and interoperability gaps that slow adoption. The bigger pattern is clear: reduce friction between data and clinicians, and outcomes improve.
If you only do one thing this month, map your data dependencies and pick one high-leverage use case to pilot alignment between 5G connectivity and AI insights. Choose a scenario with a concrete patient path, such as remote monitoring for chronic disease or rapid preoperative assessment, and set a short, measurable goal. Bold governance steps early, and you’ll avoid late-stage rework. By year-end, expect more vendors to offer open, standards-based interfaces that reduce bespoke integration pain. The roadmap is practical, not theoretical. 7 Best Amazon alexa devices with screens for small spaces in 2026
Backup strategy / What to try this week:
- audit data flows between the EHR, telehealth platform, and AI decision support system, then document latency and handoff points.
- pick one use case for a 2‑week pilot that demonstrates measurable time-to-decision gains.
- validate a governance plan covering access, consent, and audit trails before expanding.
- draft a simple vendor comparison focused on interoperability, security, and edge capabilities.
- check whether your team has a designated 5G/AI liaison to maintain momentum.