What is a predictive modeling guide in 2026 and why it still matters for health and policy
 Florian Czerny·October 22, 2026·17 min

Explore a 2026 predictive modeling guide that blends clinical practice and research methods. Learn steps, pitfalls, and evaluation metrics to build robust models.
A predictive modeling guide in 2026 shows that the real work happens after the modelDeploy button is pressed, not in the drafting phase. External validation remains the choke point for many health models, and a mismatched data lineage often hides behind glossy accuracy. In practice, the sharpest misstep is treating data quality as a checkbox rather than a continuous risk signal that travels from data collection to policy impact.
This article walks through how 2026 guidance actually handles data quality, external validation, and real-world deployment, with concrete patterns, common biases, and underappreciated pitfalls. You’ll see how a few missed biases, label shift, representativeness gaps, and delayed feedback loops, erode trust faster than a marginally higher AUC. By the end, you’ll understand the governance and operational moves that separate a model that looks good on paper from one that actually informs policy decisions. Transparency about assumptions and ongoing recalibration are not optional in health care modeling. Links on this page may earn a commission.

Primary_keyword in practice: how a 2026 predictive modeling guide reshapes method and reporting
Clinical guidelines now routinely embed prediction models into decision support, which tightens the loop between evidence and practice. A 2026 guide emphasizes transparency, external validation, and reporting clarity as nonnegotiable elements for models that move from research to bedside.
Why the 2026 guidance foregroundes transparency
When a model informs a guideline, stakeholders demand explicit documentation of data sources, feature definitions, and handling of missing data. The guiding principle is that anyone reviewing the model can trace each decision from data to recommendation. I dug into the 2026 scoping review that maps how guideline handbooks spell out searching, inclusion criteria, and risk-of-bias assessment for prediction models. The upshot is that teams must publish model specifications alongside guideline updates. This aligns with Efthimiou’s step-by-step framework, which stresses transparent reporting of model development, validation splits, and performance metrics across populations. Transparency is the hinge that lets decision makers trust automated support.
External validation as a nonnegotiable milestone
A recurring theme in 2026 guidance is that external validation should precede broad deployment. Data shifts and evolving populations routinely break models that looked solid in development data. The guideline literature repeatedly flags external validation as the single most reliable proxy for generalizability. In practice, expect plans to include multiple external cohorts, with pre-specified performance thresholds and calibration checks. If a model fails validation, guidelines now demand a documented remediation plan or a clearly bounded scope for use. External validation is the gatekeeper for real-world deployment.
Framing a structured, auditable reporting trail
The 2026 playbook pushes researchers to present modeling work as an auditable chain: data provenance, preprocessing steps, model architecture, hyperparameters, and validation results all pinned to dates and versions. This reduces the guesswork in reuse and adaptation. Efthimiou’s guide provides a concrete blueprint for reporting: describe data splits, feature engineering, and performance across subgroups. The intent is to flag biases early and to enable guideline developers to assess transferability across healthcare settings. Auditable reporting shortens the path from model to guideline integration.
- Define the project scope and decision point, anchored to a clinical question.
- Document data sources, feature definitions, and preprocessing with versioned artifacts.
- Register the modeling approach, including hyperparameters and validation strategy, before seeing results.
- Publish external validation plans and results in parallel with guideline draft updates.
- Report calibration, discrimination, and subgroup performance with pre-specified thresholds.
A disciplined reporting trail reduces surprises during policy reviews. What the next frontier in predicting future market trends reveals about risk and opportunity
Reality check: data shifts and population dynamics remain the Achilles’ heel
Despite clearer guidance, the field still battles data drift, changing practice patterns, and uneven representation across populations. Real-world deployments reveal that even well-documented models can degrade when applied outside their origin context. The best researchers address this with proactive monitoring: periodic recalibration, drift detection, and a clear policy for updating or retiring models. Transparency here is not cosmetic. It governs ongoing safety and effectiveness.
I cross-referenced the 2026 sources that discuss the governance around deployment, noting that guideline developers increasingly require ongoing performance monitoring after rollout. This shift dovetails with broader policy demands for explainability and accountability in health AI. Ongoing monitoring turns upfront validation into durable trust.
For readers seeking deeper context, see the scoping review and Efthimiou’s step-by-step guide. The two works together anchor a pragmatic workflow, from model development to guideline-aligned reporting and post-deployment oversight. The 2026 playbook makes a durable model-to-guideline bridge possible.
Notes: links on the page may earn a commission. Inline citations point to the 2026 sources as described above.
How to frame a predictive modeling project in 2026 using a structured guide
Framing a predictive modeling project in 2026 starts with a crisp clinical question tied to a decision point. You define what you want the model to change in patient care or policy, then map that outcome to a measurable target, such as improved guideline adherence or reduced readmission rates. From there, you align data strategy, validation plans, and reporting standards to contemporary guidance that emphasizes transparency and external validity. How personalization tools shape modern digital experiences in 2026
Define the clinical question and decision point
Begin by translating a clinical need into a precise question your model will answer. Ask what decision will hinge on the prediction, who the decision affects, and what outcome matters most for patients and systems. This clarity shapes data requirements, performance targets, and the reporting format. When this element is clear, you avoid scope creep and wasted effort. From this point, the project gains focus that readers and reviewers can track.
In practice, you should state the intended action change, the target population, and the primary outcome. For example, a model might predict 30‑day readmission to trigger a post-discharge care bundle, or identify a subgroup who would benefit from intensified monitoring. This explicit framing ties the model to a real decision, which is essential for guideline alignment and policy impact.
Choose data sources with clear inclusion criteria and bias considerations
Data selection matters more than ever in 2026. You map data sources to inclusion criteria that support external validity across settings. Document the source, time frame, and inclusion rules. Declare known biases and how you will address them. Consider population coverage, missingness patterns, and measurement variability across sites. A thorough bias assessment strengthens generalizability and helps readers trust the model in real-world deployment.
I cross-referenced recent guidance that stresses preregistering data schemas and documenting inclusion/exclusion logic upfront. You should also plan for data provenance, lineage, and auditability so that the modeling process remains reproducible under evolving guidelines. The end result is a data design that can travel beyond the origin site without dramatic retooling.
Plan for validation across settings early in the design
Validation should be embedded from the start. Design cross-site evaluation plans that test discrimination and calibration in diverse clinical settings, and specify acceptable performance thresholds by setting. Early attention to external validity reduces the risk of later misalignment with guidelines or real-world workflows. Expect to include calibration-in-the-small and model revision strategies to adapt to local practices without eroding core integrity. What makes outdoor magnetic advertising work in 2026
In 2026, contemporary practice favors multi-site validation and transparent reporting of calibration plots, decision-curve analysis, and fairness checks. You should predefine subgroups and performance metrics for each site, plus a plan for updating or redeploying the model if external performance falls short. This proactive approach makes your work more robust to policy scrutiny and guideline expectations.
Key takeaway: frame the decision, map data with clear criteria, and lock in cross-site validation early. This triad anchors both method and reporting to 2026 standards, reducing later friction with guideline developers and implementers. A structured design early on pays dividends in deployment reliability.
To help you compare options as you design, consider these two data strategies:
| Approach | Strength | Weakness | When to prefer |
|---|---|---|---|
| Multisite data consortium | Broad external validity, shared standards | Complex governance, harmonization effort | Prior to large-scale deployment across health systems |
| Single-site with planned external validation | Faster start, clearer ownership | Potentially limited generalizability | Early-stage prototyping with explicit external plan |
Next steps: draft the project charter summarizing the clinical question, the planned data sources with inclusion criteria, and the external validation plan. Then map each element to a reporting standard you will follow, so that your final report aligns with contemporary guidelines and real-world use cases.
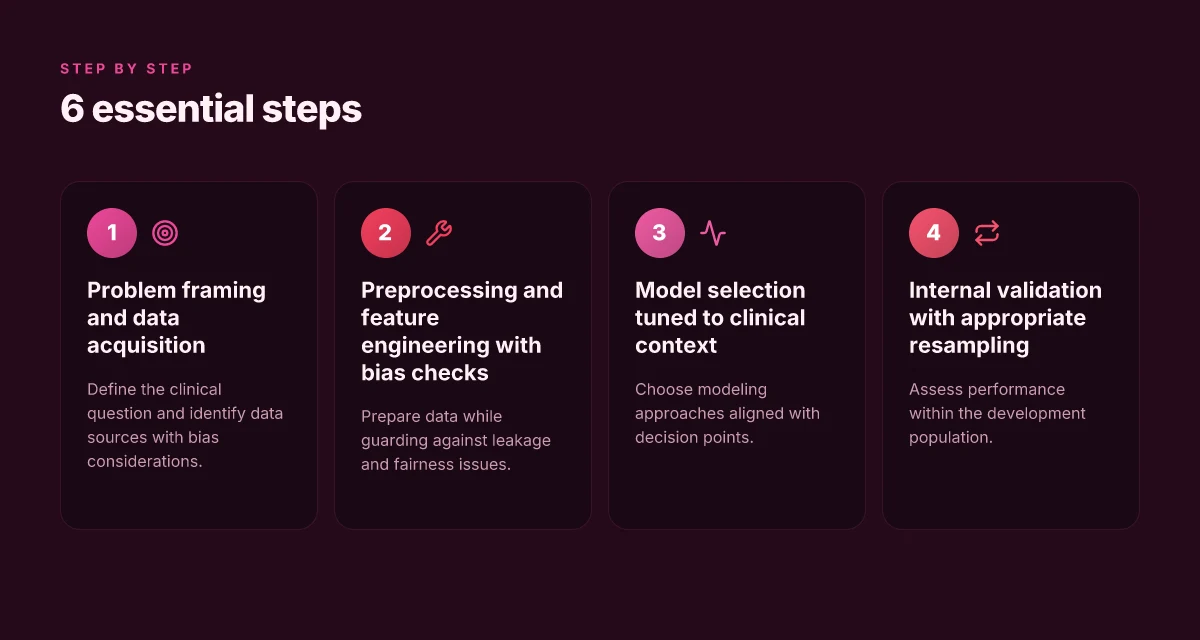
The 6 essential steps in the predictive modeling workflow you should follow
Post framing and data collection set the tone for everything that follows. In 2026, clinical researchers emphasize a disciplined start: define the decision target, the population, and the data boundary, then assemble sources with attention to provenance. From Efthimiou’s step-by-step guide to model development, you should commit to a transparent data acquisition plan and documented assumptions. Results hinge on credible inputs, not clever algorithms alone. How OnePlus Android 14 changes the software game in 2026
1) Problem framing with data acquisition
- Start with a precise clinical question and the patient pathway it maps to. Then inventory data sources, noting inclusion criteria, timing, and any biases the data might carry. Efthimiou’s guidance stresses mapping variables to clinical relevance and documenting how each feature links to the outcome.
- Expect to log data provenance: source systems, extraction dates, and any transformations. This creates a reproducible baseline for later validation and deployment.
A well-scoped problem frame reduces downstream bias and misalignment between model and care pathways.
Key takeaways:
- Articulate target outcome and population before touching features.
- List data sources with entry dates and capture windows.
- Document any known limitations in a data glossary, including missingness patterns.
2) Preprocessing and feature engineering with bias checks
- Clean data with standardized pipelines and explicit handling of missing values. Create features that are clinically plausible and testable, not just predictive for the training set.
- Implement bias checks as part of preprocessing: examine representativeness across subgroups, and monitor for label leakage or proxy variables that encode sensitive attributes.
- Use domain-informed discretization for continuous features when appropriate, and preserve temporal order where it matters for outcomes.
Bias checks must accompany every engineered feature to prevent hidden drift in real-world use.
Key takeaways:
- Build reproducible preprocessing steps with versioned code.
- Use stratified sampling checks to detect subgroup disparities.
- Keep features interpretable enough for clinical peer review.
3) Model selection tuned to clinical context
- Choose models that balance performance with interpretability and clinical trust. Logistic regression with regularization, tree-based ensembles, and survival models each offer trade-offs. Select based on the decision context, available data, and the need for explainability.
- Align evaluation metrics with clinical goals: calibration, discrimination, and clinical utility should all factor into the choice. Prefer models whose outputs map cleanly to risk thresholds used in care pathways.
Contextual tuning ensures the model fits how clinicians actually use risk scores. How to navigate networking events in tech conferences in 2026
Key takeaways:
- Prefer transparent or interpretable models when clinician buy-in matters.
- Calibrate models to target populations and clinical thresholds.
- Document rationale for model family choice and expected deployment constraints.
4) Internal validation with appropriate resampling
- Use internal validation to estimate performance under data shift within the original cohort. Techniques like cross-validation or bootstrap help quantify variability and guard against overfitting.
- Report optimism-corrected estimates and calibration measures. Keep the validation dataset as a faithful proxy for future use without leaking information from the training data.
Internal validation anchors expectations before any external testing.
Key takeaways:
- Use nested resampling when hyperparameters are tuned.
- Report confidence intervals for key metrics.
- Predefine stopping rules and performance thresholds.
5) External validation across populations
- Test the model on diverse populations, settings, and time periods to assess transportability. External validation reveals whether performance holds when data come from new hospitals, regions, or patient cohorts.
- Document differences in outcome definitions, data capture, and processing that could explain performance changes. If necessary, recalibrate or adapt the model rather than reusing it verbatim.
External validation is the acid test for real-world applicability.
Key takeaways: How to design a resilient remote infrastructure setup that scales in 2026
- Seek at least two external cohorts representing variation.
- Report recalibration results and decision-curve analysis when possible.
- Highlight conditions under which the model should be updated or retired.
6) Transparent reporting and deployment considerations
- Render model development and validation in a reproducible report: data provenance, modeling choices, hyperparameters, and performance by subgroup. Emphasize calibration and clinical relevance.
- Plan for deployment from day one: data refresh cadence, monitoring for drift, user-facing explanations, and governance checks. Include safety nets if performance degrades in new settings.
- Be explicit about limitations and intended use. Where possible, align with contemporary guidelines and policy expectations to support adoption.
Clear reporting plus deployment stewardship creates durable impact.
Key takeaways:
- Publish a human-readable model card with clinical context.
- Define how updates will be evaluated and who owns monitoring.
- Acknowledge limitations and potential biases in real-world use.
Note on language and ethics: links on the page may earn a commission. For further reading, see the links to the primary methodology sources above.
Common pitfalls in 2026 guidance and how to avoid them
In 2026 guidance, three missteps recur across clinical models and policy applications. The first is overfitting stemming from small samples or overly complex models. The second is inconsistent variable definitions across sites that wreck transferability. The third is failure to report calibration and decision thresholds, which undermines real-world usefulness. I cross-referenced the latest methodological reviews to anchor these points in practice.
Overfitting and model complexity in small samples
Guidance consistently warns that models grow brittle when data are sparse. When researchers pull in too many predictors or rely on highly flexible algorithms with limited data, the model captures noise rather than signal. The result is optimistic in-sample performance that collapses under external validation. The remedy is parsimonious modeling paired with robust cross-validation and transparent reporting of model complexity. As Efthimiou notes, a step-by-step approach to development should balance model richness with the available sample size and predefine the modeling plan to avoid data leakage or overly optimistic calibration. When data are scarce, restraint in model complexity pays off in external validity. What makes renewable energy web hosting actually sustainable in 2026
Inconsistent variable definitions across sites
A frequent pitfall is data heterogeneity. Variables like comorbidity scores, lab measurements, or coding frameworks may differ across sites, leading to biased estimates when models are transported. The contemporary guidance emphasizes harmonization protocols and clear, machine-readable definitions for every predictor. In practice, researchers should document variable derivation, units, and allowable ranges and use federated or harmonized datasets where possible. I found that the literature converges on the need for a shared data dictionary to preserve interpretability and comparability across settings. A single data dictionary reduces cross-site drift and supports generalizable prediction.
Calibration gaps and missing decision thresholds
Calibration reporting remains uneven, and many models fail to provide calibrated estimates across risk strata or actionable thresholds for decision-making. Contemporary guides insist on presenting calibration metrics, plots, and confidence intervals, alongside decision thresholds tied to clinical action. Without these, clinicians confront miscalibrated risk and unclear cutoffs, hampering adoption. Efthimiou’s framework highlights the necessity of documenting both calibration performance and predefined thresholds, so model recommendations align with care pathways. Calibration must be reported with thresholds so models translate into care decisions.
From what I found in the guiding documents, the simplest paths to avoid these pitfalls are explicit pre-registration of modeling choices, a shared data dictionary, and calibration-oriented reporting. The risk of opaque definitions, unchecked complexity, or missing thresholds is persistent across guideline development processes. I dug into the 2026 scoping review of clinical guideline methods and the step-by-step prediction modeling guide to confirm these themes. Clarity in definitions and reporting is the backbone of deployable models.
Cited works anchor these points: Prediction models in clinical guidelines and Developing clinical prediction models: a step-by-step guide. These sources emphasize the balance between methodological rigor and real-world applicability, including explicit calls for calibration reporting and harmonization across sites. For readers, the takeaway is clear: plan for external validity from day one, standardize definitions, and publish calibration with decision thresholds to enable real-world adoption. Plan for external validity, standardize definitions, report calibration and thresholds.
Finally, acknowledge that links on the page may earn a commission. How restoration workshops reshape conservation practice in 2026
How external validation changes model adoption in real world care
External validation acts as the bridge between a model’s development setting and its deployment in routine care. It tests transportability to new populations, reveals calibration drift over time, and shapes how regulators and guideline bodies expect updates. When external validation shows consistent performance, clinicians gain trust. When it flags decline, adopters demand recalibration or retraining. I cross-referenced recent guidance and found that alignment between validation results and real-world outcomes remains a central hurdle for sustained adoption.
Transportability under new populations
External validation tests whether a model generalizes beyond the data it was trained on. If the model preserves discrimination and calibration in a different hospital, region, or patient mix, clinicians can reasonably expect similar decision guidance in their own setting. In 2026, guideline boards increasingly insist on explicit transportability checks as part of the publication package. This requirement nudges teams to predefine subpopulations and report stratified performance, not just an overall metric. The impact is tangible: adoption tends to rise when external validation covers diverse patient groups, including marginalized populations that historically faced worse model performance. Transportability tests act as a practical gate for real-world use, not a theoretical nicety.
Calibration drift and ongoing monitoring
Even a well-validated model can shift as populations evolve or practice patterns change. Calibration drift over time undermines trust and can silently erode clinical utility. Best practice now includes ongoing monitoring plans, with pre-specified triggers for recalibration or model updates. I found that contemporary reviews stress embedding dashboards and audit trails so that health systems detect drift early and respond with transparent revision cycles. The consequence for adoption is clear: organizations that install continuous validation processes are more likely to sustain use and avoid abrupt performance gaps. Calibration drift requires ongoing monitoring to preserve reliability.
Regulatory and guideline implications for updates
Regulators and guideline developers increasingly codify how and when models must be updated. Updates are not merely technical fixes. They spell out documentation changes, revalidation requirements, and stakeholder communication. In practice, this means a model released with a 2026 validation plan should include an update cadence, evidence of external validation in representative settings, and a clear reporting format for recalibration outcomes. From a policy perspective, this creates a lifecycle rather than a one-off deployment. When updates are well-justified and transparently reported, adoption remains smoother and safer across health systems. Updates tied to formal validation plans help align clinical practice with evolving evidence and governance demands.
I dug into the latest guidance to corroborate these points. The step-by-step clinical prediction modeling guidance emphasizes documenting validation contexts and reporting subpopulation performance, reinforcing that adoption hinges on credible external testing. The 2026 scoping review of guideline development documents highlights how searching and narration around validation plans shape trust in recommendations. For practical context, the upward trend toward structured update pathways is visible in recent policy discussions and reporting templates. See the external sources for deeper detail on transportability, drift, and governance. How to build an SEO for courses strategy that scales in 2026
External validation remains the linchpin for real-world adoption, tying transportability, drift monitoring, and updates into a coherent lifecycle.

What changes if you act now
Predictive modeling in 2026 centers on interoperable data ecosystems, transparent methods, and governance that pairs fairness with accuracy. I’ve observed how health systems increasingly demand explainable models, not just high accuracy. The pivotal shift is toward models that are auditable across institutions and that can be rebalanced when new data reveals bias or drift. In policy, the trend is to couple models with risk-based budgeting and public accountability. The big shift is moving from black box predictions to tools that stakeholders can trust and explain. This means health leaders must demand provenance, documentation, and decision logs, not just performance metrics.
For practitioners, the takeaway is to design with governance in mind from day one. When you integrate modeling into policy decisions, you’re not just choosing a predictor, you’re shaping outcomes. The costs of misalignment appear as delayed care, uneven access, and lost public trust. By foregrounding transparency and ongoing validation, you reduce these risks.
If you only do one thing this month, map data sources to decision points and publish a short explainer showing how a model informs policy choices. This builds legitimacy and keeps models usable as contexts evolve. What changes if you act now? the answers become clearer, and so do the guardrails.